

Apr
Muscle Pain and Tendinopathy, Sports Injuries and Management
Is Plantaris A Cause Of Achilles Tendinosis?
Is It More Than Just A Hypothetical Cause Of Tennis Leg?
Tennis leg is a common injury, especially during running or jumping. It usually happens when a sudden load hits the ankle while the knee stays straight. People often describe the sensation as a sudden strike to the back of the leg. Many turn around, thinking they were hit by a racquet or ball.The plantaris muscle is one possible cause. Though small and sometimes absent, it’s often blamed. Some experts argue it tears and causes pain. Others believe it’s not involved at all.
This debate continues because symptoms vary. Imaging has shown plantaris injuries in some cases. In others, the issue may lie in the gastrocnemius muscle instead.
Still, understanding the plantaris’ potential role is key. It may not always be the cause, but it’s worth considering.
An Emerging Role In Achilles Tendon Pain
Recently, research has shifted toward the plantaris tendon’s link with Achilles pain. Many people with Achilles tendinopathy feel pain on the inner side of the tendon. This often occurs 2 to 7 cm above the heel, in the tendon’s midsection.
In the past, overpronation was blamed. This inward foot motion puts stress on the tendon’s medial side. But newer studies suggest another cause—the plantaris tendon.
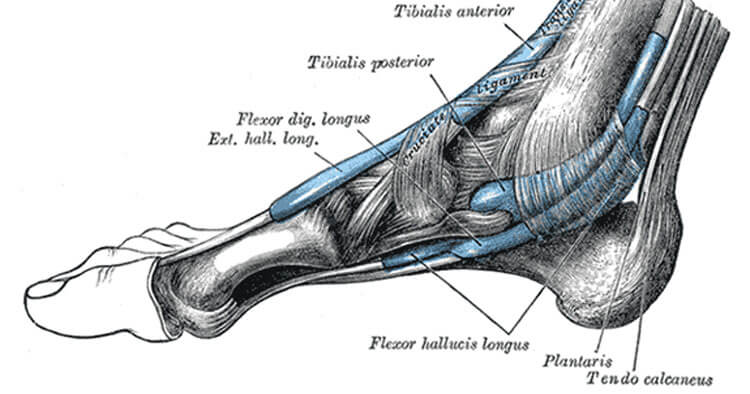
It lies close to, and sometimes within, the Achilles tendon. This proximity can cause friction. If the two tendons rub or move differently, pain can follow.
In some people, it inserts separately into the heel bone. In others, it blends into the Achilles. These differences might help explain why some experience pain, and others don’t.
Anatomy Of The Plantaris Tendon And Achilles Tendon Pain
The tendon runs along the inner edge of the Achilles. It travels down the calf, often ending near the heel.
Though small, it can impact Achilles function. Some anatomical studies show it’s stiffer and stronger than the Achilles. This stiffness might pull on the Achilles and cause irritation.
In people with mid-portion Achilles tendinopathy, scar tissue and adhesions often form where the plantaris and Achilles sit close together. This can make the tendons stick or rub during movement.
Histology supports this theory. Tissue samples sometimes show new blood vessels and nerve fibers. These changes are linked to pain.
The plantaris might not be passive. It could contribute to persistent symptoms in certain cases.
The Plantaris Hypothesis As A Cause Of Mid Tendon Medial Achilles Tendinosis
The hypothesis suggests that a thickened plantaris tendon can compress the Achilles. This might lead to stress, inflammation, or degenerative change.
Studies from Sweden, including work by Alfredson et al., support this theory. Some patients improved after surgeons removed the plantaris tendon. These were people who had long-term pain and didn’t respond to conservative care.
Ultrasound often shows a thickened plantaris in these cases. Some treatments—like eccentric loading or guided injections—can help. But when these fail, surgery becomes a valid option.
These findings have prompted a shift. Now, clinicians are more likely to consider its involvement, especially in chronic, medial-sided Achilles pain.
More Research Required
Despite these findings, much remains unknown. The plantaris muscle is still considered vestigial by many. But the evidence suggests it plays a bigger role than once thought.
Clinicians should keep it in mind. When medial Achilles pain doesn’t improve, it’s worth assessing plantaris involvement.
Non-insertional Achilles tendinopathy causes around 66% of all Achilles issues. If the plantaris plays a part, better treatments could follow.
We also need more research on its mechanics. What does the plantaris do during walking or running? Does it help or hinder calf function? These questions remain open.
The answers could help runners, jumpers, and anyone with persistent Achilles pain.
Disclaimer: This information is provided as an educational service and is not intended to serve as a substitute for personalized medical advice. Sydney Physio Clinic does not endorse any treatments, procedures, products mentioned in this post. Anyone seeking specific advice, or assistance regarding the “plantaris muscle” should consult his, or her physiotherapist, orthopaedic surgeon, general practitioner, sports medicine specialist, or otherwise appropriately skilled medical practitioner.
